Acute exacerbations of asthma and chronic obstructive pulmonary disease (COPD) represent a persistent gap in respiratory care, with millions of patients experiencing life-threatening episodes each year. While existing biologics can manage chronic inflammation, they fail to address the urgent therapeutic needs of these sudden attacks.

Barry Quart, PharmD
Chief Executive Officer
Connect Biopharma
In this Innovation Spotlight, Barry Quart, the chief executive officer and director of Connect Biopharma, highlights the need for better acute exacerbation treatments and introduces rademikibart, a humanized monoclonal antibody that, via a dual inhibition strategy, may offer a faster and more effective intervention than current treatment options.
What is the overall burden of COPD and asthma?
Asthma and COPD represent a significant burden on patients and the broader healthcare system. According to the Asthma and Allergy Foundation of America, in 2013, the total financial cost of asthma in the United States was approximately $82 billion. It is estimated that from 2019-2038, the total cost of asthma will reach nearly $964 billion. The cost of COPD is estimated to be $24 billion annually in the US. More than 22 million adults are affected by asthma in the US, and 30-40% experience at least one exacerbation annually. COPD affects more than 16 million people, with 30-50% experiencing at least one exacerbation per year. Acute exacerbations reflect serious clinical and economic consequences. For patients, the events can be life-threatening, and for the healthcare system, exacerbations are extremely costly.
What are acute exacerbations, and why are they so difficult to treat?
Acute exacerbations, also called episodes or attacks, are sudden and severe worsening of respiratory symptoms, including coughing, wheezing, and shortness of breath, which can lead to hospitalization or death. Each year, over one million asthma patients and 1.3 million COPD patients visit an emergency department for exacerbations. Acute exacerbations remain a critical unmet need, as there are no biologics currently approved for therapeutic use. Available biologics are effective only for maintenance and fail to address the therapeutic gap for treating acute exacerbations. These treatments can also take from weeks to months to improve symptoms, without considering the dire timing needed for potentially fatal exacerbations. Medical care utilization remains high, with about 50 percent of patients experiencing a worsening of an exacerbation or another exacerbation within a few weeks of discharge.
Although the inflammatory pathways that drive these exacerbations are well understood from a biological standpoint, conducting clinical trials in the emergency department setting is difficult compared to studying patients with stable disease in the clinic setting.
What is your strategy for treating these inflammatory lung disorders?
IL-4 and IL-13 are cytokines that are critical for the type 2 helper T cell (Th2) inflammatory pathway. Their downstream signaling causes a range of physiological processes, including airway muscle contraction and eosinophilic inflammation, and is responsible for driving inflammatory conditions, such as asthma, COPD, and other immune-related diseases. Rademikibart addresses the two major components of Type 2 disease: IL-4-driven IgE and inflammatory signals, and the IL-13-driven mucus hypersecretion, bronchoconstriction and tissue remodeling. This dual-action mechanism provides a comprehensive approach to treating severe Type 2 inflammatory diseases.

Rademikibart targets the IL-4Rα subunit to block IL-4 and IL-13 signaling, offering a potential rapid-onset approach to treating acute exacerbations in asthma and COPD.
©iStock, milan2099
What is the mechanism of rademikibart, and how does it help?
Rademikibart is Connect Biopharma’s lead program. It is a humanized monoclonal antibody engineered to target interleukin-4 alpha receptor (IL-4Rα), which is a common subunit for IL-4 and IL-13 receptors. Interactions with other subunits result in an increase of Th-2 mediated responses that are responsible for disease progression. Rademikibart binds to IL-4Rα and prevents both the receptor from interacting with other subunits and signaling by IL-4 and IL-13 cytokines. This dual blockage at the receptor level, instead of targeting individual cytokines, is a mechanistically efficient and differentiated approach to suppressing Th2-driven inflammation across multiple disease states.
This mechanism is relevant to both asthma and COPD, due to the physiological role of Th2-mediated inflammation in these conditions. By targeting the IL-4Rα subunit, rademikibart can address the inflammatory conditions that are relevant to acute exacerbations in both asthma and COPD. Data published in the American Journal of Respiratory and Critical Care Medicine highlight that rademikibart’s mechanism gives rise to a rapid onset of action, which greatly distinguishes the candidate from other biologics that either require weeks or months to achieve meaningful symptomatic benefit.1
Where is rademikibart in the pipeline, and what sets this drug apart from others in development?
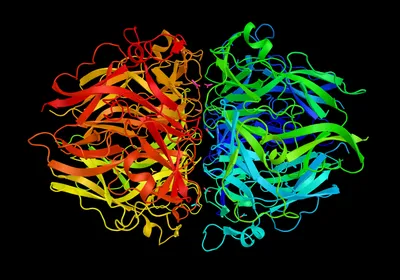
Rademikibart’s unique binding ability gives rise to the clinical differentiation in treating acute exacerbations, including a rapid onset of airway function improvement, coupled with an improved safety profile. In addition, rademikibart has shown dose-dependent and differentiated pharmacokinetics and pharmacodynamics in clinical trials. Data published in SKIN: The Journal of Cutaneous Medicine show that rademikibart provides a molecular and structural rationale for the enhanced IL-4Rα inhibition compared to other treatments that target inflammatory diseases, further evidencing rademikibart’s promising potential as a next-generation treatment.2
While approved biologics are used for maintenance therapy, no options have demonstrated a benefit as a treatment for inflammatory episodes and attacks. As such, there are currently no biologics approved for treatment of acute exacerbations. Rademikibart has the potential to be the first therapy approved for treating acute exacerbations, addressing a significant need for large patient populations.
What response have you received from clinicians?
Clinicians have a keen interest in new treatments for acute exacerbations, as there have been no new treatments in decades. In addition to strong interest in the potential use of rademikibart for acute treatment of exacerbations, clinicians overwhelmingly indicated that if a patient responded well to acute treatment, they would keep the patient on rademikibart chronically as well.
How do you see the landscape of inflammatory disease treatment evolving?
The treatment of chronic asthma and COPD has well-established trial methodologies; however, there is a different challenge for treating acute exacerbations, as the timing and stage of symptoms remain the most critical standpoint. Acute exacerbations remain a large unmet medical need and are largely underexplored.
Rademikibart represents a novel shift in how the healthcare field is beginning to target this population, not as a maintenance therapy, but as a distinct therapeutic for treating acute exacerbations. The amplification of rademikibart and the progression through clinical trials will help increase awareness of the necessity for a treatment to address this significant unmet need and large patient population.
- Kerwin E, et al. Rademikibart treatment for moderate-to-severe uncontrolled asthma: a Phase 2B randomized clinical trial. Am J Respir Crit Care Med. 2025;211(5):749-758.
- Shi Y, et al. Optimized second-generation IL-4RΑ inhibition: Structural and molecular dynamics properties of rademikibart FAB-IL-4RΑ complex. SKIN. 2024;8(6):s452.